Karkhana, Secunderabad Mon–Sat, 11:30 am – 5:00 pm  ·  formerly BNR Skin & Vitiligo Hospital ★ 5.0 on Practo · 10,000+ patients treated →
Home›Vitiligo›Types and stages
Vitiligo

Vitiligo stages and types

Vitiligo has no numbered stage one to four. Dermatologists stage it by activity, spreading, stable or repigmenting, using the VIDA score, and classify it by pattern: focal, segmental or non-segmental. Those two readings decide almost everything about treatment, including whether surgery is possible.

At a glance

Stages
Active, stable, repigmenting: by VIDA score
Active
New or expanding patches within 12 months
Stable
No change for 12 months: the surgical gate
Focal
One or a few patches; pattern not yet declared
Segmental
One side, one nerve territory, young onset
Non-segmental
Symmetrical, both sides, most common
The two patterns

One side, or both sides.

This is the first thing a dermatologist decides, and it changes almost everything that follows. Segmental disease keeps to one side of the body and stops at the midline. Non-segmental appears in matched pairs — the same site on both sides.

Two simplified featureless human figures side by side on brown skin. The left figure has pale depigmented patches gathered into a single band running down one side of the face, trunk and arm, stopping abruptly at the midline so the other half is unaffected. The right figure has smaller patches arranged symmetrically — a matching patch at each eye, each elbow, each hand and each knee.
  1. 1
  2. 2
  3. 3
  4. 4
  1. 1One side only
  2. 2Stops at the midline
  3. 3Matched on both sides
  4. 4Hands, face, knees

Segmental disease usually becomes stable within a year and is the pattern that responds best to surgical repigmentation. Non-segmental is the immune-driven form, and controlling the immune attack comes before anything else.

  1. One side only
  2. Stops at the midline
  3. Matched on both sides
  4. Hands, face, knees

Illustration, not a photograph.

Before you decide

Who is treating you, and what his patients said.

Dr. (Lt Col) Khagendra Varada, dermatologist and dermatosurgeon

Dr. (Lt Col) Khagendra Varada

  • 45 years in dermatology and dermatosurgery
  • 25 of them in the Indian Army Medical Corps
  • MBBS, Osmania Medical College
  • Dip. Practical Dermatology, Cardiff · Dip. Dermatology, AAAM

Reg. No. 10461, Hyderabad State Medical Council

Full background →

“I have been going pillar to post to get my son cured of his white spot on his left side of lip and chin. It appeared 8 years back. I was told it’s special type of nerve vitiligo which has no cure. After reporting to him he told us that it is SEGMENTAL VITILIGO and unlikely and difficult to be cleared by medications alone. He suggested for surgical melanocyte transplant… I was amazed after around one month that he started rapidly getting pigmentation. I wholeheartedly suggest please do not waste time like I did.”

★★★★★Gunaganti Madaru · Google

“Dark spots are seen in one month… Even before perticular treatment for vitiligo, great”

★★★★★Manojkumar Kalapala · Google
Read all 70 stories →
By pattern

Segmental or non-segmental

These behave so differently that they are almost two conditions sharing one name.

About 90% of cases

Non-segmental vitiligo

Symmetrical, if it appears on one knee it tends to appear on the other. Comes and goes in waves over years, often starting on the hands, face, or around the eyes and mouth.

  • Both sides of the body
  • Unpredictable course
  • Autoimmune associations more common
  • Responds to phototherapy
About 10% of cases

Segmental vitiligo

Confined to one side, often following a nerve territory, and usually starting in childhood or adolescence. It spreads quickly for six to twenty-four months, then typically stops for good.

  • One side only
  • Early onset
  • Burns out and stabilises
  • The best candidate for surgery
By pattern, side by side

Focal vs segmental vs non-segmental vitiligo

Focal is where most vitiligo starts and it is not a third disease: it is the label for one or a few patches before the pattern has declared itself. Most focal vitiligo turns out to be early non-segmental disease; some turns out to be segmental; a little stays focal for years.

FocalSegmentalNon-segmental
WhereOne or a few patches, no pattern yetOne side of the body, often along a nerve territory, stopping at the midlineBoth sides, in matched pairs: hands, face, elbows, knees
WhoAny ageUsually children and young adultsAny age; the commonest form, about nine in ten cases
CourseWatched; may stay put or evolve into either patternSpreads within its segment for six to twenty-four months, then usually stops for goodComes and goes in waves over years
ProgressionCannot be predicted from the first patch; dated photographs decide itPredictable: burns out and stabilisesUnpredictable; activity is re-judged at every review
TreatmentTopicals; excimer for a patch or two; re-classified as it declaresResponds poorly to light; the best candidate for grafting once stableImmune control first, then narrowband UVB; surgery for stubborn stable sites

A report that says ‘focal vitiligo’ is a provisional label, not a verdict. The useful question is whether the patch has moved since it was first photographed.

Segmental vitiligo is the surgical success story

Because it stabilises reliably and rarely returns, segmental disease is where grafting gives its most durable results. It also responds poorly to phototherapy, so recognising it early saves patients months of light treatment that was never going to work.

Reading the edge

The border tells you what it is doing.

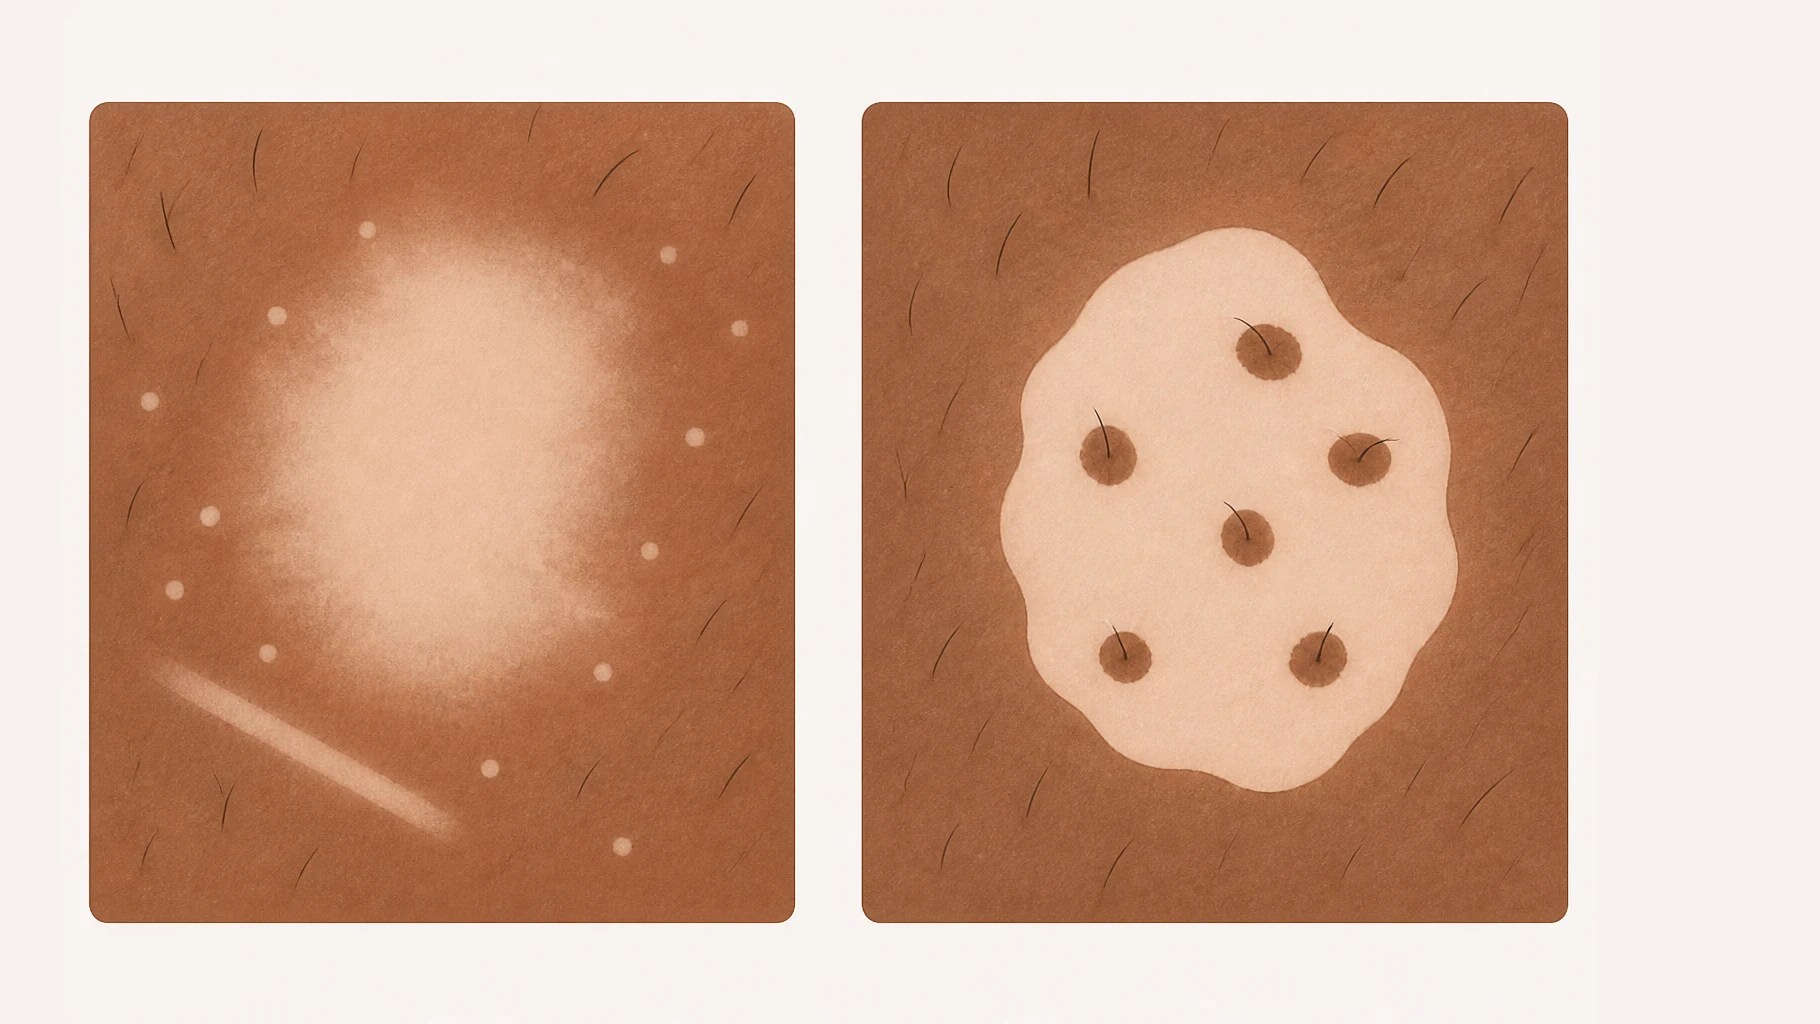
Whether the disease is currently spreading is read from the margin of the patch, not from how large it is. An advancing edge fades; a settled one is drawn.

Two areas of brown skin seen from above. The left patch has a soft ill-defined border fading gradually into the surrounding skin, with tiny separate pale dots scattered outside it and one straight pale streak crossing the skin nearby. The right patch has a single crisp border, no scattered dots, and several small round islands of returning brown pigment inside it, each centred on a hair.
  1. 1
  2. 2
  3. 3
  4. 4
  5. 5
  1. 1Border fades out
  2. 2Confetti spots
  3. 3A scratch line
  4. 4A border you can draw
  5. 5Pigment at each hair

This is why the twelve-month wait before surgery is not caution for its own sake. Grafting into active disease means the same immune process destroys the transplanted cells.

  1. Border fades out
  2. Confetti spots
  3. A scratch line
  4. A border you can draw
  5. Pigment at each hair

Illustration, not a photograph.

The stages

Stages of vitiligo

There is no stage one to four. The staging that decides treatment is by activity, and the score dermatologists use for it is VIDA, the Vitiligo Disease Activity score: it asks only how recently the disease last moved.

StageVIDAWhat you seeWhat it means for treatment
First patch—One or a few patches; the pattern has not declared itselfExamined under the Wood’s lamp; baseline photographs; treated medically
Active, fast+4 to +3A new patch or spread within the last six weeks to three months; blurred edges, confetti spots, patches along scratchesStop the spread first; nothing is rebuilt while this continues
Active, slow+2 to +1The last change was between three and twelve months agoMedical control continues; the twelve-month clock has not run
Stable0No new patch and no spread for at least twelve monthsRepigmentation with light; surgery becomes possible
Repigmenting−1Stable, and colour returning on its own: islands of pigment around each hairThe best position to treat from; light and topicals consolidate it
UniversalanyOver four-fifths of the skin has lost pigmentRepigmentation is impractical; evening out the last colour is discussed instead

VIDA is a clinical score, from the history and the examination. It is not a blood test, and it is not the same as how much skin is affected: a small patch can be active and a large one stable.

By activity

Active or stable: the real question

Every treatment decision hangs on this. Active disease must be quietened before anything is rebuilt; stable disease can be rebuilt, including surgically. Getting it wrong in either direction wastes months.

There is no blood test for stability. It is a clinical judgement made from the history, the appearance of the patch margins, and, most reliably, photographs taken at intervals and compared properly.

What the lamp shows

More patches than you can see.

A Wood’s lamp is a handheld ultraviolet light. Under it, skin that has lost pigment fluoresces bright chalk-white with a sharp border, while normal skin stays dark — so patches that are invisible in ordinary light, and edges that look vague, both become obvious.

The same patch of brown forearm skin shown twice. In ordinary daylight two pale patches are faint and low in contrast with soft edges. Under a handheld lamp casting a violet glow, the same two patches stand out as sharp-edged chalk-white areas — and three more patches are visible that could not be seen at all in daylight.
  1. 1
  2. 2
  3. 3
  4. 4
  1. 1Two faint patches
  2. 2Under the lamp
  3. 3The same two, sharp
  4. 4Three more

This is how the true extent of the disease is judged, and how a vague-looking border is confirmed as genuinely advancing. It is also the examination most often skipped.

  1. Two faint patches
  2. Under the lamp
  3. The same two, sharp
  4. Three more

Illustration, not a photograph.

Telling them apart

What suggests active disease

SignWhat it meansWhat it changes
New patches in 6 monthsThe disease is producing fresh lesionsStop the spread before repigmenting
Blurred, ill-defined edgesThe patch is expanding outwardSurgery deferred
Trichrome appearanceA pale zone between normal and white skinMarker of ongoing activity
Koebner phenomenonNew patches where skin was cut or scratchedA strong argument against grafting now
Confetti-like maculesSmall scattered spots around a patchSuggests rapid progression
White hairs in the patchFollicular pigment reserve is depletedMedical repigmentation less likely to work

None of these is decisive alone. A Wood’s lamp examination and dated photographs together are how the judgement is actually made.

The stability clock

Why twelve months, and not six.

Grafting into disease that is still active does two things, both bad: the transplanted cells are attacked like the original ones, and the donor site can develop its own patch.

Twelve months without a new patch, without expansion at any margin, and without koebnerisation is the accepted threshold. It is not an arbitrary wait. It is the interval that separates a graft that takes from a graft that fails.

What graft surgery involves

The clock restarts

One new patch in month ten resets the count. This is frustrating and it is also the honest answer.

Photographs settle it

Dated images at fixed distance and lighting are worth more than anyone’s recollection of what the patch looked like last year.

Other patterns you may be told

Terms that appear in reports.

  • Focal: one or a few patches, not yet classifiable
  • Acrofacial: face plus fingers and toes
  • Mucosal: lips and genitals; notoriously stubborn
  • Universal: over 80% of the body depigmented
  • Trichrome: three shades in one patch; a sign of activity
  • Halo naevus: a pale ring around a mole; often coexists
Questions patients actually ask

Types and stages

What are the stages of vitiligo?

Vitiligo is staged by activity rather than by number. Active disease has produced a new patch or spread within the last twelve months; the VIDA score grades how recently, from +4 for the last six weeks down to +1 for the last year. Stable disease has not changed for twelve months, scored 0, and repigmenting disease is stable with colour returning on its own, scored −1. Surgery is only considered at 0 or −1.

What is the difference between focal and segmental vitiligo?

Focal vitiligo is one or a few patches with no pattern yet; it is a provisional label. Segmental vitiligo keeps to one side of the body, often along a nerve territory, spreads within that segment for a year or two and then usually stops. A focal patch on one side may become segmental; a focal patch that later pairs up on the other side has declared itself non-segmental.

Does focal vitiligo spread?

Sometimes, and it cannot be predicted from the first patch. That is why the first visit records it under the Wood’s lamp and photographs it at a fixed distance: the next set of photographs answers the question that the first cannot.

How do I know if my vitiligo is stable?

If no new patch has appeared and no existing patch has grown for twelve months, and cuts or scratches have not turned white, it is likely stable. It is confirmed clinically with a Wood’s lamp and by comparing dated photographs. Not by how it feels to you.

Which type of vitiligo responds best to treatment?

Non-segmental vitiligo on the face and trunk responds best to phototherapy. Segmental vitiligo responds poorly to light but does very well with surgery once it has burnt out.

Does segmental vitiligo spread to the rest of the body?

Typically not. It spreads within its segment for six to twenty-four months and then usually stops permanently. That predictability is what makes it a good surgical candidate.

What is the Koebner phenomenon?

New vitiligo appearing exactly where the skin was injured: a cut, a scratch, a burn, a tight strap. It is a marker of active disease and an argument against operating until things settle.

Can the type change over time?

Segmental disease does not usually become non-segmental. But a person can have both, and focal disease that has not declared itself may evolve into either, which is why the first classification is sometimes provisional.

References

The clinical statements on this page follow the guidance and evidence below. They are independent sources. None of them is connected to this clinic, and none of them sells the treatments described here.

  1. Vitiligo: overview, causes and treatmentUS National Institute of Arthritis and Musculoskeletal and Skin Diseases (NIH)
  2. VitiligoDermNet (New Zealand Dermatological Society)
  3. Vitiligo: overview and diagnosisAmerican Academy of Dermatology
  4. Consensus-based guidelines for surgical management of vitiligo, Vitiligo Task Force, IADVL Academy 2024–2025Indian Journal of Dermatology, Venereology and Leprology

The first appointment is a diagnosis.

Not a treatment plan sold on the spot. Message the clinic and bring your history.

Book on WhatsApp Call